Retinitis Pigmentosa: How to Recognize It on the Fundus, FAF and ERG
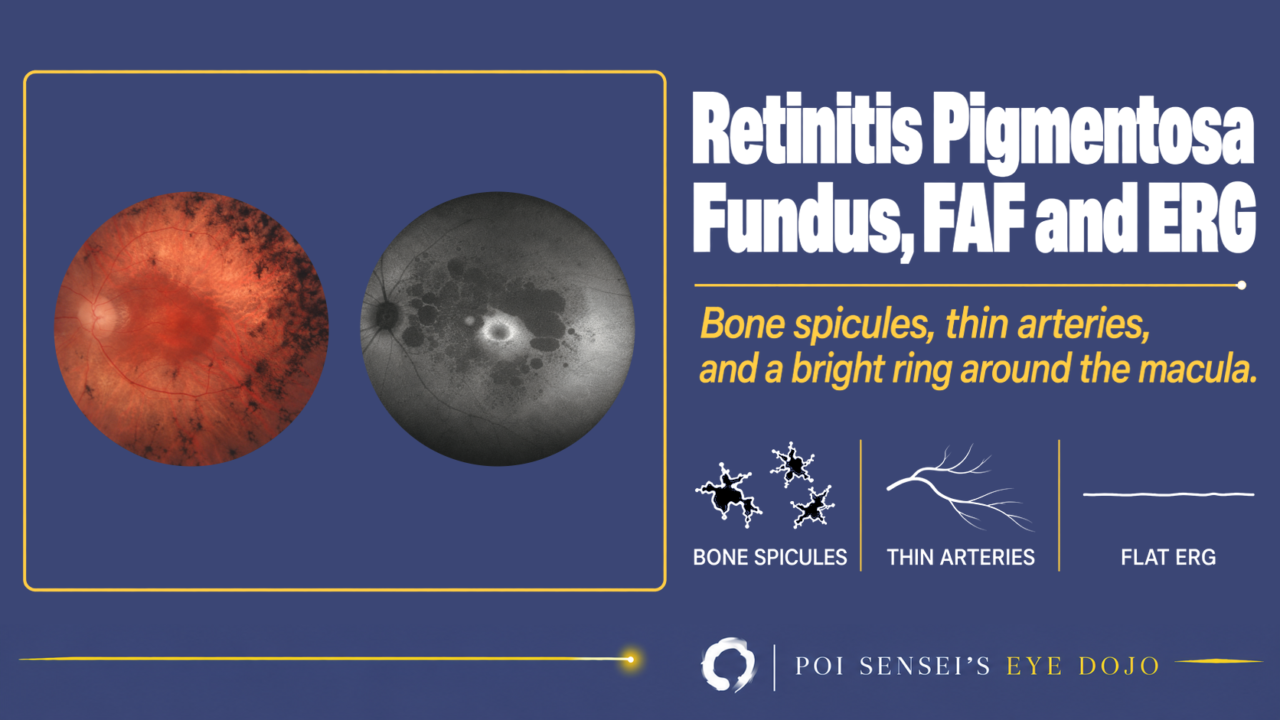
A patient has had trouble seeing in the dark for years, and the fundus shows black pigment in the mid-periphery. Think of retinitis pigmentosa (RP). This article shows how to recognize RP on the fundus, fundus autofluorescence (FAF) and the electroretinogram (ERG), including eyes that have almost no pigment.
- Night blindness came first, and the visual field has slowly narrowed.
- Both eyes show bone-spicule pigment in the mid-periphery.
- The retinal arteries are thin, and you cannot follow them out to the periphery.
- The rod response and the mixed response are reduced, or the ERG is flat.
What is retinitis pigmentosa?
Retinitis pigmentosa is an inherited degeneration of the photoreceptors. The rods are damaged first and the cones later, so it is a rod-cone dystrophy.
Rods handle vision in the dark, and they are damaged first over a wide area, so night blindness comes early. Then the visual field narrows from the mid-periphery, slowly, over years to decades. Visual acuity from RP itself falls late, when the central cones are lost, but cataract or CME can lower it earlier.
RP is the most common inherited retinal dystrophy, affecting about 1 in 3,000 to 5,000 people. Autosomal recessive inheritance is common, but RP can follow any pattern: autosomal dominant, X-linked or mitochondrial. Many patients have no affected relatives[1].
Findings
Fundus
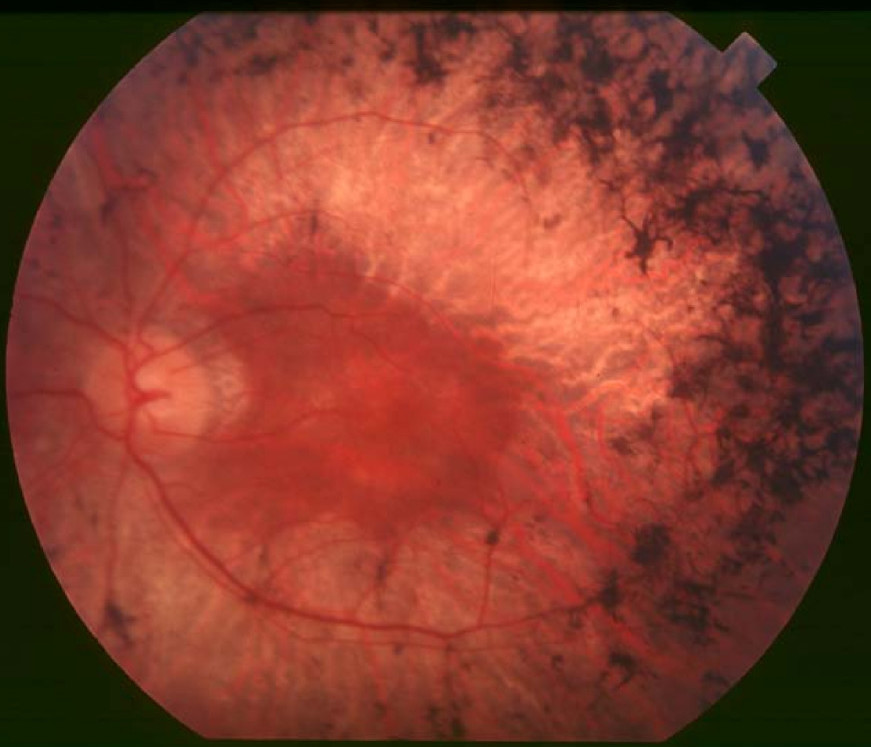
The typical fundus shows three things in both eyes:
- Bone-spicule pigment (black, branching clumps) in the mid-periphery
- Mottled retinal pigment epithelium (RPE), which gives the fundus an uneven color
- Narrow retinal arteries
The optic disc may also look pale and waxy.
Syphilis can cause an RP-like fundus, so testing for it is sometimes worthwhile[1].
RP without pigment
Some patients have no typical bone spicules. This is called RP sine pigmento, and the fundus can look almost normal at first glance. In early RP there is no pigment yet, because the pigment appears only after the photoreceptors have degenerated.
Two findings still point to RP: the thin arteries, and the ring on FAF (below). A wide-field fundus photograph makes the thin arteries easier to see.
Fundus autofluorescence
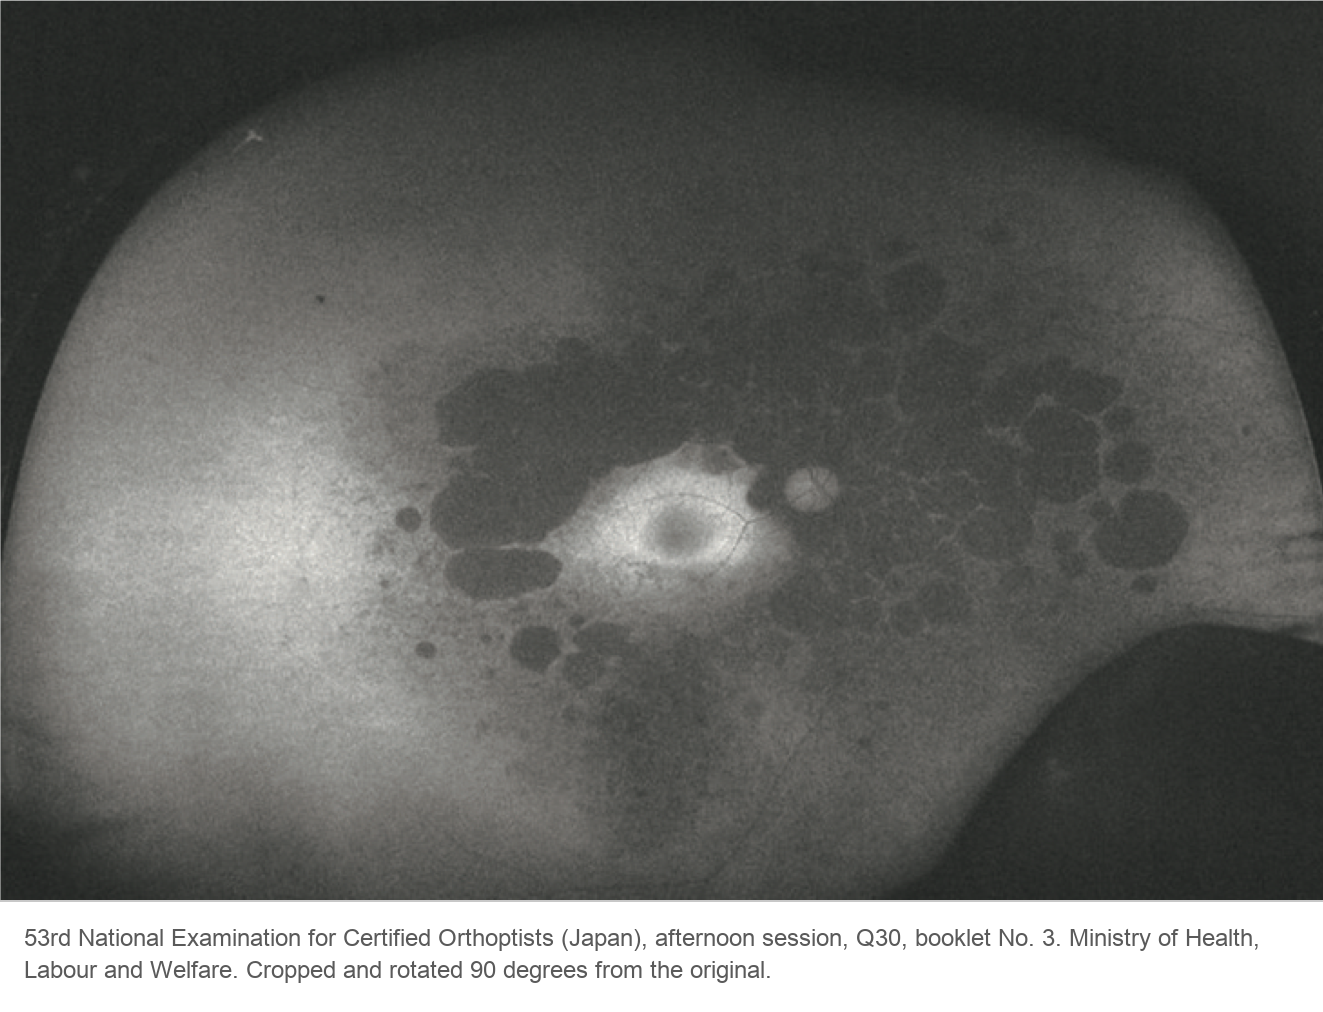
FAF shows dark patches in the mid-periphery, where the RPE has become atrophic. There is often a bright ring at the border between the atrophic periphery and the macula, which is still alive[1].
ERG
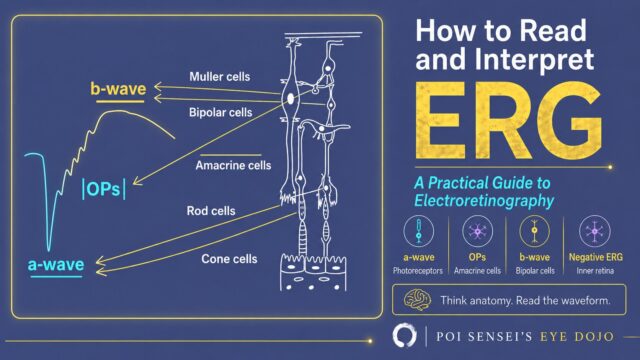
Early in RP, the rod response and the mixed response (rods and cones together; dark-adapted 3.0 ERG) become smaller. The cone responses fall later. In advanced RP, the ERG is flat.
When the history and the fundus of both eyes are typical, you can make the diagnosis without an ERG. The ERG matters most when the fundus looks nearly normal, as in RP without pigment or in young relatives of a patient. The rod responses fall even before the retina looks abnormal[2].
The full-field ERG adds up the response of the whole retina. So it can be nearly flat while the macula still gives good visual acuity. Patients with an unrecordable ERG can often still read[3].
OCT
OCT shows thinning of the outer retina. The ellipsoid zone (EZ), the line made by the photoreceptors, fades from the edges of the scan toward the center.
This change is easy to miss unless you look for it. Even when the scan looks normal at a glance, follow the EZ from one edge of the scan to the other.
Complications and cautions
Cataract
Posterior subcapsular cataract is common. Cataract surgery helps, but plan it with care. The zonules can be weak. After surgery, the capsule tends to contract strongly, and the inflammation is often strong.
Macular edema and epiretinal membrane
Cystoid macular edema (CME) and epiretinal membrane are common. CME may respond to carbonic anhydrase inhibitors (CAIs): oral acetazolamide or topical drops[1]. Oral acetazolamide has more side effects, such as tingling of the hands and feet, fatigue and kidney stones, so topical drops are often tried first.
If CME does not improve, steroids are an option: eye drops, a sub-Tenon or intravitreal injection of triamcinolone, or a dexamethasone implant. Both CAIs and steroids can reduce the edema, but the gain in visual acuity is limited. Anti-VEGF injections thin the macula but have not improved acuity, so they are not recommended[4].
Sildenafil
Treatment
There is no treatment that stops RP. For RP caused by mutations in both copies of the RPE65 gene, gene therapy with voretigene neparvovec (Luxturna) is approved in the US (2017), the EU (2018) and Japan (2023)[4]. Genetic testing finds these patients, and it can also open the way to clinical trials.
Treat cataract and CME when they occur. Low-vision aids help. High-dose vitamin A has been tried, but there is no consensus that it helps[1].
Systemic diseases with RP
RP can be part of a systemic syndrome.
| Syndrome | Look for |
|---|---|
| Usher | Hearing loss |
| Bardet-Biedl | Extra fingers, kidney disease |
| Refsum | Ichthyosis, neurological signs. Treated with diet |
| Bassen-Kornzweig | Ataxia, fat malabsorption. Treated with vitamins |
| Kearns-Sayre | Ptosis, eye movement limits, heart problems |
Kearns-Sayre syndrome shows a salt-and-pepper retina, most striking at the macula. Other associations include the mucopolysaccharidoses (Hunter, Hurler and Scheie), Batten disease and Cockayne syndrome[1].
Summary
- RP is an inherited rod-cone dystrophy: night blindness first, then a slowly narrowing field, and loss of acuity late.
- The fundus shows bone-spicule pigment, mottled RPE and thin arteries. If you cannot follow the arteries out to the periphery, think of RP.
- Without pigment, look for thin arteries and a bright FAF ring around the macula, which is still alive.
- The ERG shows reduced rod and mixed responses early and becomes flat later, sometimes while the patient can still read.
- Watch for cataract with weak zonules and CME, and send patients for genetic testing.
Figure credits
Fundus photograph: Figure 2 from Hamel C. Retinitis pigmentosa. Orphanet J Rare Dis 2006;1:40, via Wikimedia Commons, licensed under CC BY 2.0. Unchanged.
Fundus autofluorescence: 53rd National Examination for Certified Orthoptists (Japan), afternoon session, question 30, booklet No. 3. Ministry of Health, Labour and Welfare. Cropped and rotated 90 degrees from the original, with the source added below the image.
References
[1] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 15, Inherited retinal degenerations: retinitis pigmentosa.
[2] Yanoff M, Duker JS, eds. Ophthalmology. 5th ed. Elsevier; 2019. Chapter 6.14, Progressive and "stationary" inherited retinal degenerations; Chapter 6.45, Retinal toxicity of systemically administered drugs.
[3] Hamel C. Retinitis pigmentosa. Orphanet J Rare Dis. 2006;1:40. PMID 17032466.
[4] Japanese Ophthalmological Society. Guidelines for the management of retinitis pigmentosa 2026. Nippon Ganka Gakkai Zasshi. 2026;130(4):376-398. In Japanese.
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.