Cone Dystrophy: Symptoms, Fundus, OCT and ERG Findings
A young patient’s central vision is slowly getting worse, bright light is uncomfortable, and the fundus looks almost normal. Think of cone dystrophy. This article explains what cone dystrophy is, and how to read the fundus, OCT and ERG that make the diagnosis.
- Central vision falls slowly in both eyes, often before age 20.
- Bright light is uncomfortable (photophobia), and color vision is poor.
- The macula shows a bull’s eye pattern, or looks almost normal.
- On the ERG, the cone response and 30 Hz flicker are reduced, while the rod response is relatively preserved.
What is cone dystrophy?
Cone dystrophy is an inherited retinal dystrophy in which the cones slowly degenerate across the whole retina. In retinitis pigmentosa, the rods are affected first and the cones later. In cone dystrophy, the cones are affected first.
In some patients, the rods are also affected after the cones. This is called cone-rod dystrophy. The two are almost the same disease, and in practice it is hard to draw a clear line between them[1].
Symptoms
Vision loss, a central scotoma, photophobia and color vision defects usually start before age 20, but many patients first notice them as adults. Photophobia is typical from the early stage[1]. The disease progresses slowly in both eyes.
Cone function is normal at birth, so nystagmus is usually absent. This is different from achromatopsia, a cone disorder present from birth. Night blindness early in the course suggests cone-rod dystrophy, because the rods are involved too[2].
Inheritance
It can be autosomal dominant, autosomal recessive or X-linked, and more than 30 genes have been found[3]. Some of them also cause other macular dystrophies. For example, ABCA4 also causes Stargardt disease[1].
Fundus
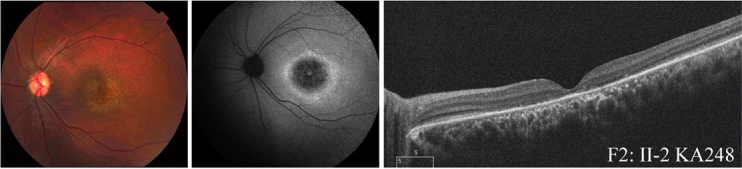
The classic finding is a bull’s eye maculopathy, a ring of atrophy around the fovea. It is easier to see on fundus autofluorescence (FAF) than on a color photograph. On FAF, the atrophy is dark, often with a bright ring at its edge[1].
The fundus varies a lot. It can look completely normal, show nonspecific atrophy at the macula, or show atrophy across the whole posterior pole. You cannot diagnose cone dystrophy from fundus images alone[1].
A bull’s eye is not specific to cone dystrophy either. Chloroquine maculopathy and advanced Stargardt disease can look similar[3].
OCT
The ellipsoid zone becomes faint and is then lost, and the outer retina gets thinner[1].
ERG findings
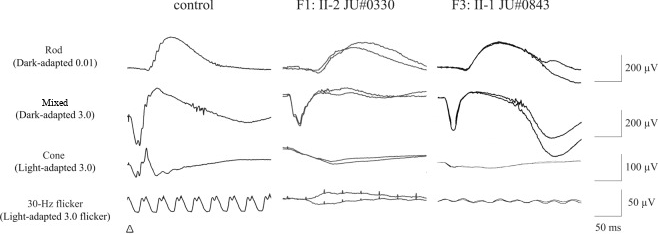
Because the fundus can look normal, the diagnosis rests on the ERG. A full-field ERG that records the rod and cone responses separately shows that cone function is lost across the whole retina[1].
DA means dark-adapted and LA means light-adapted. The number is the flash strength.
| ERG step | Cone dystrophy |
|---|---|
| Rod (DA 0.01) | Normal early |
| Mixed response (DA 3.0) | Normal or mildly reduced early |
| Cone (LA 3.0) | Reduced, then absent |
| 30 Hz flicker | Reduced, then absent |
The 30 Hz flicker flashes 30 times a second. Rods cannot follow this speed, so only cones respond. That is why it drops in a cone disease. First, each wave peaks later than normal (a prolonged peak time). Then the waves get smaller[2]. As the disease progresses, the cone response and the 30 Hz flicker are lost.
While only the cones are affected, the rod response is normal. The mixed response comes from rods and cones together, but after dark adaptation most of it comes from the rods. So the mixed response stays normal or is only mildly reduced[4].
In cone-rod dystrophy, the rods are affected later, and the rod and mixed responses get smaller too[4]. When the rods and cones are lost across the whole retina, the ERG becomes flat, as in advanced retinitis pigmentosa.
Treatment and prognosis
There is no treatment that stops the disease. Low vision care, such as magnifiers, is important.
Vision usually becomes poor over time, and the speed of progression varies widely between patients[3].
Summary
- Cone dystrophy is an inherited retinal dystrophy in which the cones degenerate first. When the rods follow, it is called cone-rod dystrophy.
- Vision loss, photophobia and color vision defects usually start before age 20.
- The classic fundus is a bull’s eye, clearer on FAF, but the fundus can look normal.
- ERG: the cone response and 30 Hz flicker fall, while the rod and mixed responses are relatively preserved.
- There is no treatment. Low vision care is important.
Figure credits
Fundus, FAF, OCT and ERG: Figures 2 and 3 from Mizobuchi K, Hayashi T, Katagiri S, et al. Sci Rep 2019;9(1):16851 (https://doi.org/10.1038/s41598-019-52660-1), licensed under CC BY 4.0. Figure 2 cropped to one patient. Figure 3 cropped to the lower panel, and the row label "Combined" changed to "Mixed".
References
[1] Working Group for the Diagnostic Guidelines for Macular Dystrophy. Diagnostic guidelines for macular dystrophy. Nippon Ganka Gakkai Zasshi. 2019;123(4):424–442. In Japanese.
[2] Gill JS, Georgiou M, Kalitzeos A, Moore AT, Michaelides M. Progressive cone and cone-rod dystrophies: clinical features, molecular genetics and prospects for therapy. Br J Ophthalmol. 2019;103(5):711. PMID 30679166.
[3] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 15, Inherited retinal degenerations: Cone and cone-rod dystrophy.
[4] Robson AG, Nilsson J, Li S, et al. ISCEV guide to visual electrodiagnostic procedures. Doc Ophthalmol. 2018;136(1):1–26. PMID 29397523.
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.