Macular Telangiectasia Type 2 (MacTel): Fundus and OCT Findings
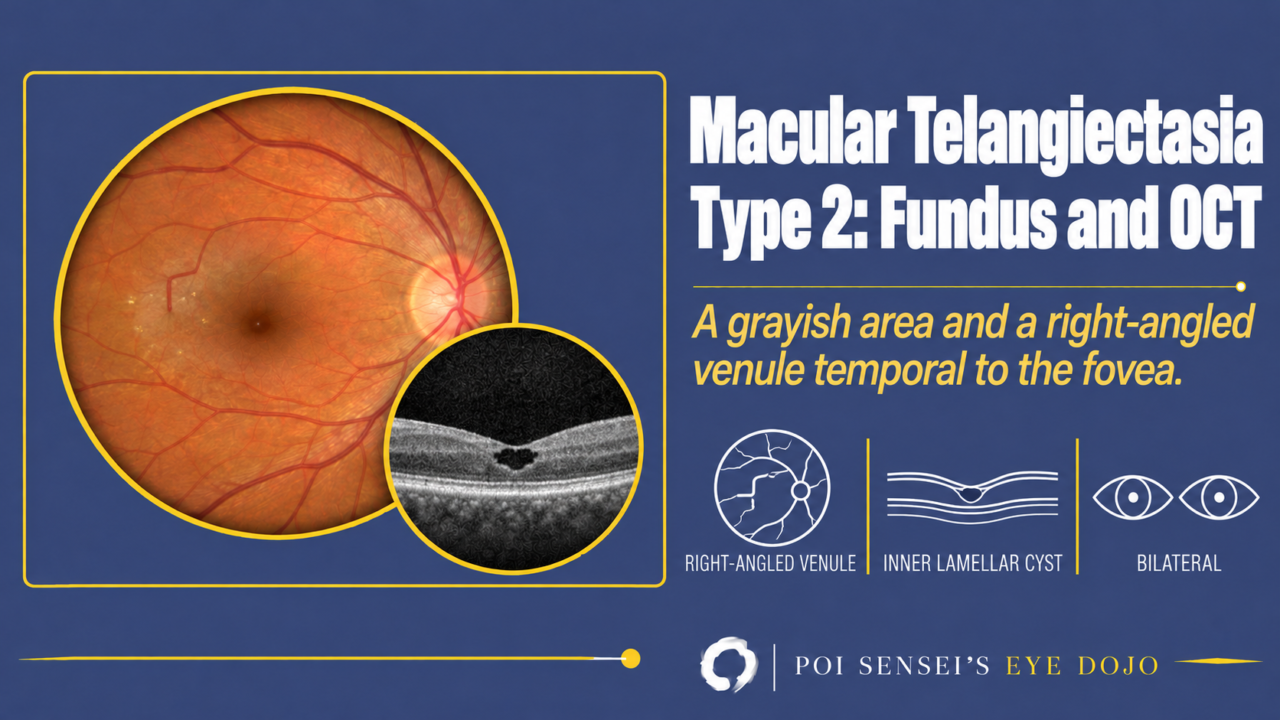
A patient in their 50s or 60s notices that vision in both eyes has slowly become blurred. There is a grayish area temporal to the fovea, and OCT shows a small cavity under the fovea. Think of macular telangiectasia type 2 (MacTel). This article explains how to read the fundus, fluorescein angiography and OCT, what to tell it apart from, and how it is treated.
- Vision falls slowly in both eyes in middle age.
- The retina temporal to the fovea looks grayish, with a vein that turns at a right angle.
- OCT shows a cavity in the inner retina under the fovea and a break in the ellipsoid zone.
- Fluorescein angiography leaks temporal to the fovea, but there is no macular edema.
MacTel has a type 1 and a type 2, but they are not two forms of one disease. Think of them as two completely different diseases.
What is MacTel type 2?
Onset is usually in the 50s or 60s. Unlike type 1, there is no sex difference, and almost all cases are bilateral. Type 2 is common in Western countries and rare in Japan, where type 1 is seen more often.
Both types show dilated capillaries at the macula, but the cause is different. Type 1 is a congenital anomaly of the capillaries. In type 2, degeneration of the retinal Müller cells is thought to come first, and the capillaries dilate secondarily[1]. The cavity seen on OCT, the inner lamellar cyst, is also thought to come from this Müller cell degeneration.
Fundus and fluorescein angiography
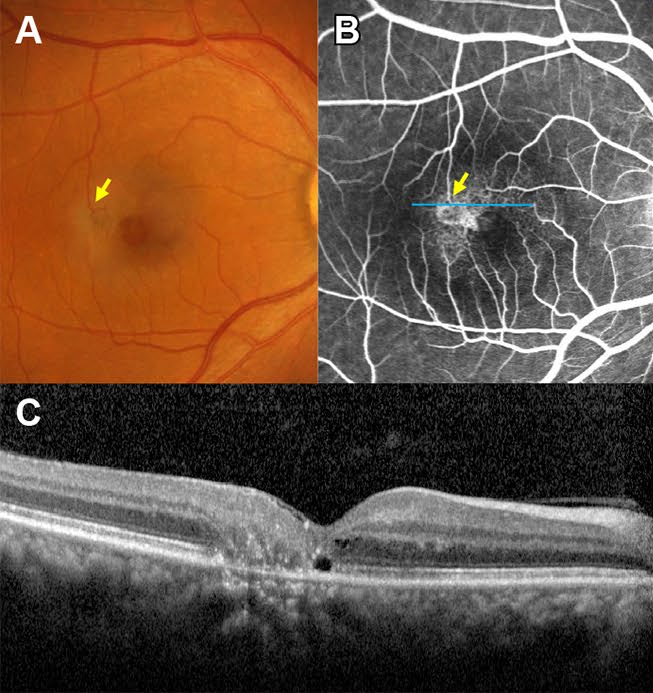
Early changes are subtle. The retina temporal to the fovea loses its transparency and looks grayish. Fine crystalline deposits are common.
As the disease progresses, a small retinal vein turns at a right angle and dives into the deep retina. This is called a right-angled venule. Pigment clumps often form at its tip. Intraretinal pigment and a macular hole can also develop[1].
On fluorescein angiography, the dilated capillaries temporal to the fovea are easier to see than on the fundus photograph. They leak, but they do not cause cystoid macular edema.
OCT
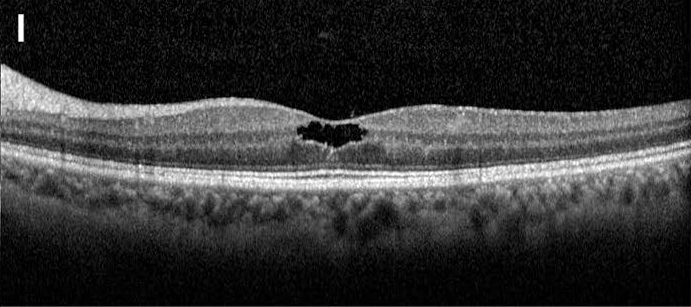
At the fovea, OCT shows a cavity within the inner retina, called an inner lamellar cyst. It often grows as the disease progresses. The ellipsoid zone (EZ) is a bright OCT band that comes from the photoreceptors. A break in the EZ can be seen from early in the disease.
Differential diagnosis
When subretinal neovascularization develops, it must be told apart from neovascular age-related macular degeneration (AMD).
Even without neovascularization, vision can fall from loss of the EZ at the macula. The fundus may then look almost normal, so the differential includes occult macular dystrophy.
Treatment
No treatment restores vision that has been lost. Anti-VEGF injections are used only when neovascularization develops[1].
A treatment to slow the disease is now available. In March 2025, an eye implant that releases ciliary neurotrophic factor (revakinagene taroretcel) was approved in the United States. It is the first approved treatment for MacTel type 2, and it slowed the loss of the EZ[2].
Summary
- MacTel type 1 and type 2 are different diseases. Type 1 is a congenital capillary anomaly, and type 2 is thought to start with Müller cell degeneration.
- Type 2 is bilateral, with onset usually in the 50s or 60s.
- Fundus: a grayish area temporal to the fovea, then right-angled venules and pigment.
- OCT: an inner lamellar cyst and a break in the EZ. The cavities are not macular edema.
- Treatment: anti-VEGF only for neovascularization. An implant that slows EZ loss was approved in the United States in 2025.
Figure credits
Fundus, fluorescein angiography and OCT: Figure 1 from Chung YR, Kim YH, Oh J, et al. Sci Rep 2021;11(1):17198 (https://doi.org/10.1038/s41598-021-96789-4), licensed under CC BY 4.0. Panels A to C cropped for the first figure, and panel I for the second.
References
[1] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 14, Acquired macular disorders: idiopathic macular telangiectasia.
[2] Hoy SM. Revakinagene taroretcel: first approval. Mol Diagn Ther. 2025;29(4):553-561. PMID 40540142.
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.