NAION vs Arteritic AION: How to Tell Them Apart
An older patient wakes up with blurred vision in one eye, and the optic disc is swollen. This is most likely anterior ischemic optic neuropathy (AION), and the first thing to decide is whether it is arteritic. Arteritic AION comes from giant cell arteritis and needs steroids the same day to protect the other eye. Non-arteritic AION (NAION) is far more common and has no proven treatment.
This article goes through how to tell the two apart, which drugs to ask about, and where posterior ischemic optic neuropathy fits.
Three types of ischemic optic neuropathy
Ischemic optic neuropathy is divided into anterior ischemic optic neuropathy (AION), with swelling of the optic disc, and posterior ischemic optic neuropathy (PION), without it.
AION is further divided into two:
- Arteritic AION (AAION), caused by giant cell arteritis
- Non-arteritic AION (NAION), caused by poor blood flow to the disc without inflammation
| AAION | NAION | PION | |
|---|---|---|---|
| Disc | Pale swelling | Sectoral swelling | Normal at first |
| Main cause | Giant cell arteritis | Vascular risk | Blood loss |
| Age | About 70+ | About 60 | Any |
| Systemic signs | Headache, jaw pain, high ESR/CRP | Few | Depend on cause |
| Treatment | IV steroid pulse, same day | None proven | Treat the cause |
Arteritic AION: giant cell arteritis
AAION happens when inflammation blocks the arteries that feed the optic nerve.
The main cause is giant cell arteritis (GCA), also called temporal arteritis. Rarely, other vasculitides such as ANCA-associated vasculitis can cause it.
Symptoms and findings
GCA almost never starts before age 50, and most patients are around 70 or older. Women are affected about four times as often as men.
Vision drops suddenly in one eye. As in other optic neuropathies, the eye has a relative afferent pupillary defect (RAPD) and a reduced critical flicker fusion frequency (CFF). Brief episodes of blurred vision before the attack point strongly to the arteritic form.
Ask about the symptoms outside the eye:
- Pain or tenderness over the temporal artery
- Pain in the jaw when chewing (jaw claudication)
- Scalp tenderness, sometimes noticed when combing the hair
- Fatigue, fever and weight loss
GCA is a systemic inflammatory disease, so the erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) are usually raised. A normal ESR does not rule it out: it is normal in about one in five patients. A high platelet count also points to GCA.
The optic disc is swollen, but strikingly pale ("chalky white") for the amount of swelling. Vision loss is usually severe, and the field defect can take any shape, including an altitudinal defect (loss of the upper or lower half of the field).
Diagnosis
The diagnosis rests on temporal artery biopsy. Do not wait for the biopsy to start steroids.
The inflammation is not continuous along the artery. It comes in patches, called skip lesions, so take a long segment. If the first biopsy is negative and the picture still fits, a biopsy from the other side may be needed. The American College of Rheumatology (ACR) recommends a segment longer than 1 cm, taken within 2 weeks of starting steroids.
Ultrasound of the temporal artery, which shows a dark "halo" around the lumen, is another option. European recommendations accept it in place of biopsy, while the ACR still prefers biopsy in the United States[1].
Treatment
Treatment is high-dose steroids, started the same day. When vision is threatened, intravenous methylprednisolone pulses come first, followed by oral prednisolone at about 1 mg/kg per day.
Vision in the affected eye rarely comes back, even with prompt treatment. The steroids are there to protect the other eye. Without treatment, about one-third of patients with AAION lose the second eye as well, usually within a week.
GCA tends to flare as steroids are tapered, and long-term steroids cause their own problems. Tocilizumab, an antibody against the interleukin-6 receptor, cuts the steroid needed, and the ACR suggests considering it from the start in newly diagnosed GCA[1].
GCA can come with polymyalgia rheumatica (PMR): severe pain and stiffness of the shoulders and upper arms, worse on waking, so bad that some patients cannot turn over in bed. It responds dramatically to steroids.
Non-arteritic AION (NAION)
NAION is ischemia of the optic disc from poor flow in the short posterior ciliary arteries, without inflammation.
Patients are typically around 60, about ten years younger than in AAION, and often have vascular risk factors such as hypertension and diabetes.
Symptoms
The typical complaint is sudden, painless loss of the upper or lower half of the vision in one eye (an altitudinal defect), such as "I can’t see the lower half." When the loss is altitudinal, it is the lower half in about 75–80% of eyes[2].
It is often noticed on waking. Blood pressure is lowest during sleep, and this nocturnal dip is thought to play a part. Sleep apnea is also a risk factor.
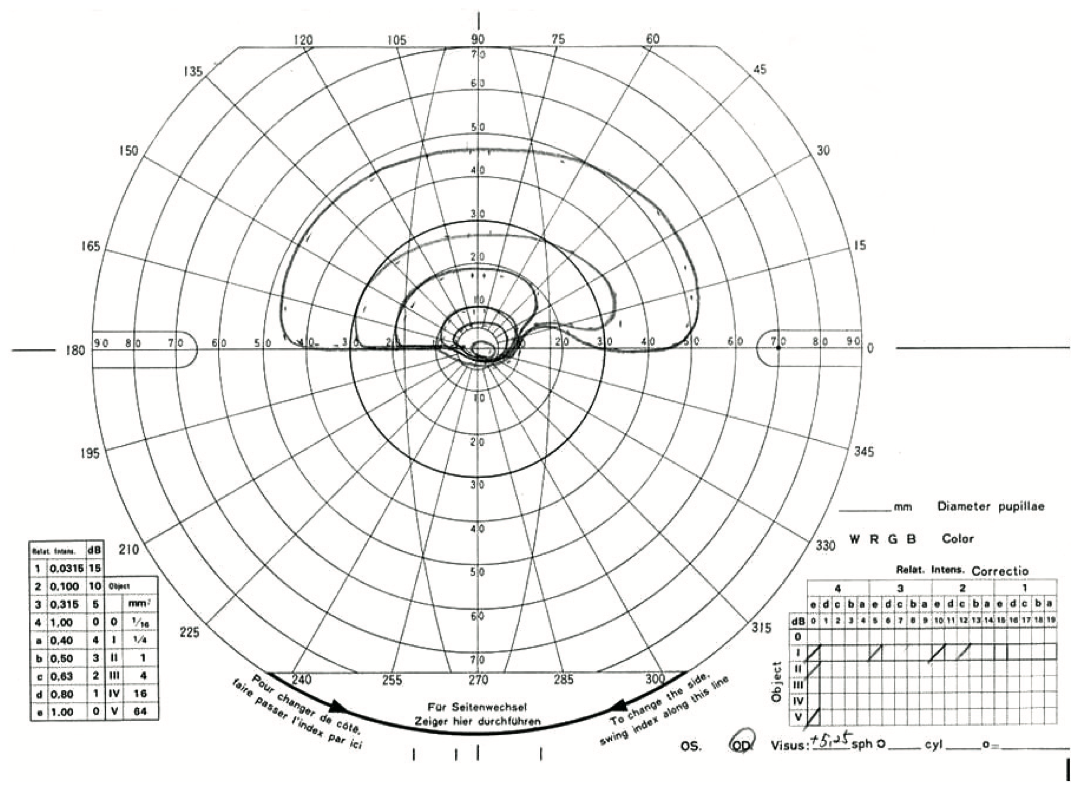
A 70-year-old man with treated hypertension, a long-time smoker, noticed blurred vision in his right eye on waking. The right eye had an RAPD. In the visual field of the right eye, the upper half is kept and the lower half is lost, cut off along the horizontal line: an inferior altitudinal defect.
The optic disc
The disc is swollen, often sectorally: one part, usually the upper or lower half, is more swollen than the rest. The swelling is usually hyperemic (red rather than pale), and flame-shaped hemorrhages at the disc margin are common.
NAION can also cause diffuse swelling, as in optic neuritis. But when you see sectoral swelling, think of ischemia first.
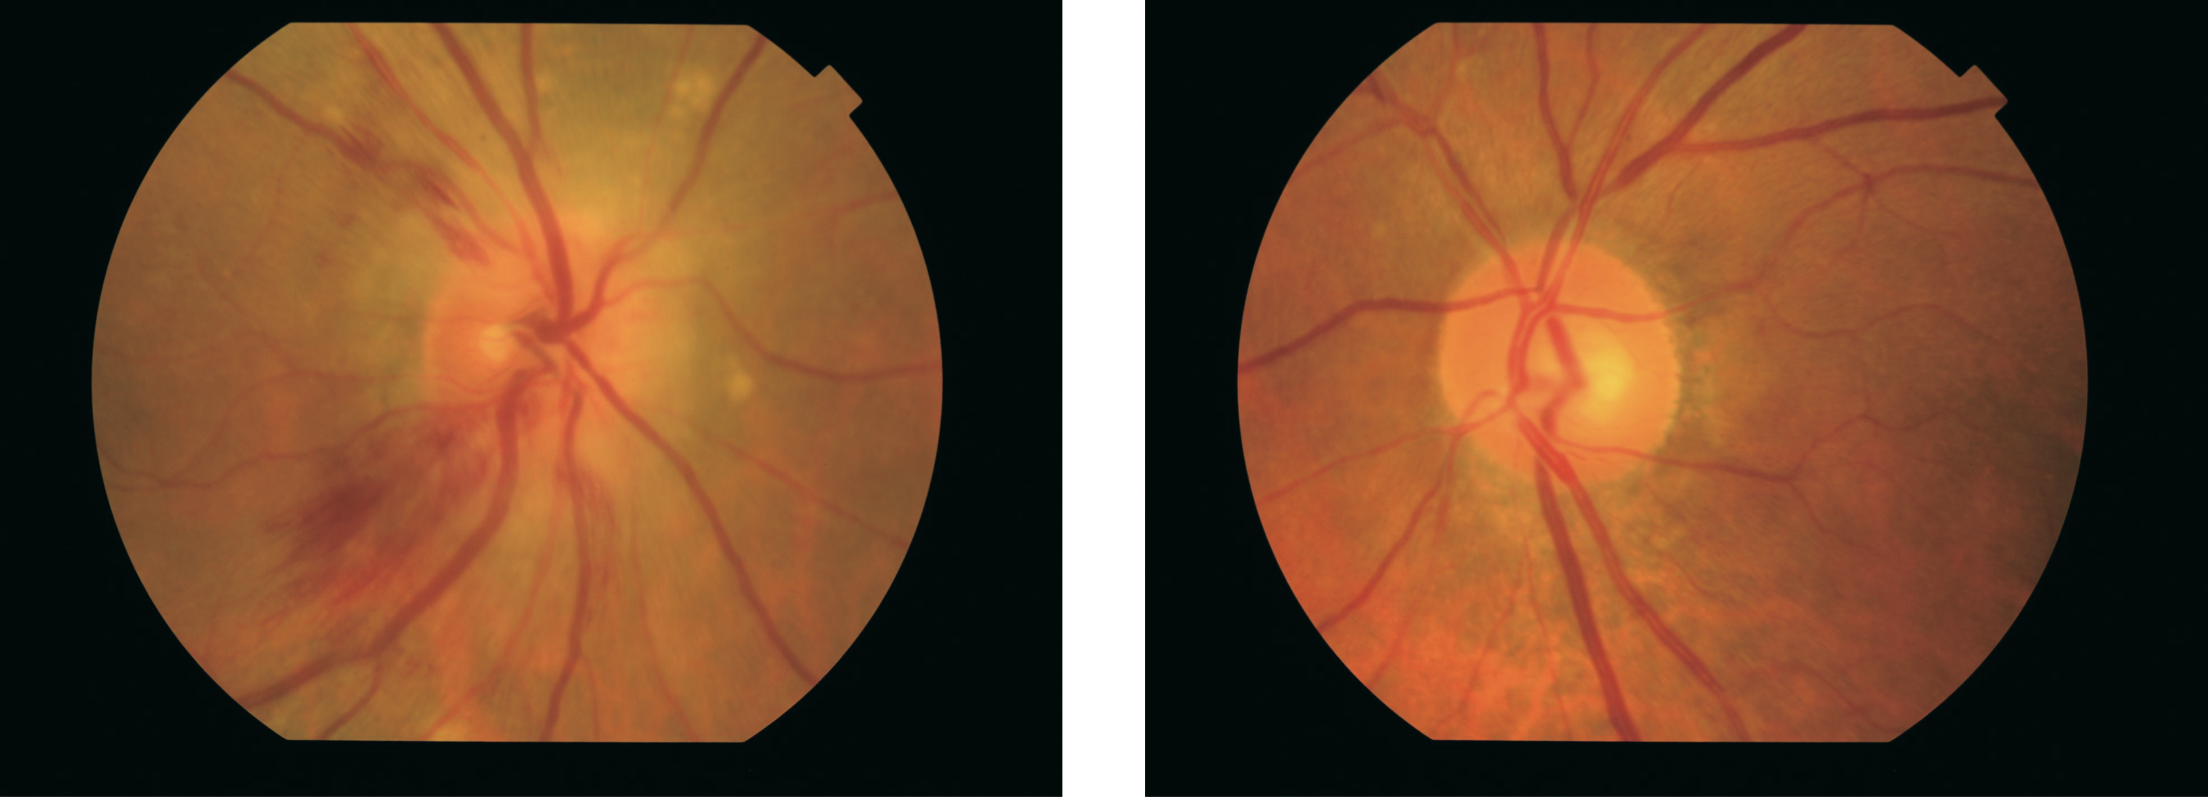
The same patient as above. The right optic disc is swollen, with blurred margins and flame-shaped hemorrhages at its edge.
OCT angiography is increasingly used to look at blood flow in the disc.
Causes
Beyond hypertension and diabetes, NAION can follow:
- Severe anemia, shock, or heavy blood loss in surgery
- Antiphospholipid syndrome (suspect it in a woman with lupus or recurrent miscarriage)
- Drugs (next section)
AION can also complicate Vogt-Koyanagi-Harada disease when the disc is swollen. In a Japanese series of 52 patients, 6 of the 15 with disc swelling were left with permanent field defects from AION. Most were older, and four had a small disc with little or no cup[3].
Drugs to ask about
Two kinds of drugs have been linked to NAION: drugs for erectile dysfunction (PDE5 inhibitors) and semaglutide, a GLP-1 receptor agonist for diabetes and obesity.
| Drug | Brand | What the label or regulator says |
|---|---|---|
| Sildenafil | Viagra | About 2-fold risk when taken within the previous 5 half-lives; causal link not proven[4] |
| Tadalafil | Cialis | Same class warning; causal link not proven[5] |
| Semaglutide | Ozempic, Rybelsus, Wegovy | Very rare (up to 1 in 10,000); about 2-fold risk in type 2 diabetes[6] |
Treatment
Unfortunately, no treatment has been proven to restore vision. Treat the vascular risk factors. Aspirin is often given for general vascular protection, but it does not seem to lower the risk in the other eye. The fellow eye is affected in about 15% of patients within 5 years.
Posterior ischemic optic neuropathy (PION)
PION is ischemic optic neuropathy without disc swelling. Most cases are non-arteritic, but GCA can rarely cause it.
The commonest non-arteritic cause is heavy blood loss in surgery or trauma, especially in spine and heart surgery. Vision drops suddenly, in one or both eyes. The field defect varies: altitudinal loss, a central scotoma or general constriction. The disc looks normal at first and turns pale over weeks.
AION comes from the short posterior ciliary arteries. PION comes from the pial capillary plexus around the nerve behind the eye, fed by branches of the ophthalmic artery.
Summary
- Older patient with sudden vision loss and a swollen disc: decide first whether it is arteritic.
- If AAION is suspected, start IV steroid pulses the same day; do not wait for the biopsy.
- NAION: altitudinal loss noticed on waking, sectoral swelling, and a disc at risk in the other eye.
- Ask every NAION patient about PDE5 inhibitors and semaglutide.
References
[1] Maz M, Chung SA, Abril A, et al. 2021 American College of Rheumatology/Vasculitis Foundation Guideline for the Management of Giant Cell Arteritis and Takayasu Arteritis. Arthritis Rheumatol. 2021;73(8):1349–1365. PMID 34235884.
[2] Hayreh SS, Zimmerman B. Visual field abnormalities in nonarteritic anterior ischemic optic neuropathy: their pattern and prevalence at initial examination. Arch Ophthalmol. 2005;123(11):1554–1562. PMID 16286618.
[3] Nakao K, Mizushima Y, Abematsu N, Goh N, Sakamoto T. Anterior ischemic optic neuropathy associated with Vogt-Koyanagi-Harada disease. Graefes Arch Clin Exp Ophthalmol. 2009;247(10):1417–1425. PMID 19568763.
[4] Pfizer. VIAGRA (sildenafil citrate) tablets. US prescribing information, section 5.3 Effects on the Eye (revised 12/2017). https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=0b0be196-0c62-461c-94f4-9a35339b4501
[5] Eli Lilly. CIALIS (tadalafil) tablets. US prescribing information, section 5.4 Effects on the Eye. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=bcd8f8ab-81a2-4891-83db-24a0b0e25895
[6] European Medicines Agency. PRAC concludes eye condition NAION is a very rare side effect of semaglutide medicines Ozempic, Rybelsus and Wegovy (6 June 2025). https://www.ema.europa.eu/en/news/prac-concludes-eye-condition-naion-very-rare-side-effect-semaglutide-medicines-ozempic-rybelsus-wegovy
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.