Axenfeld-Rieger Syndrome: Posterior Embryotoxon, Iris Changes and Glaucoma
A white line runs just inside the limbus in both eyes, and strands of iris reach it. Think of Axenfeld-Rieger syndrome. This article explains how to tell Axenfeld anomaly, Rieger anomaly and Rieger syndrome apart, and why glaucoma is the main problem.
What is Axenfeld-Rieger syndrome?
Axenfeld-Rieger syndrome is an autosomal dominant developmental anomaly of the front of the eye (anterior segment dysgenesis). It comes from abnormal development of tissues that form from neural crest cells. Both eyes are usually affected.
Axenfeld-Rieger syndrome is the name for the whole spectrum. It is divided by the findings:
- Axenfeld anomaly = posterior embryotoxon with iris strands
- Rieger anomaly = Axenfeld anomaly + iris changes
- Rieger syndrome = Rieger anomaly + systemic anomalies, such as dental and facial anomalies
Findings
Axenfeld anomaly
Axenfeld anomaly shows posterior embryotoxon. In the normal angle, the Schwalbe line is the white line where Descemet membrane ends, at the border between the cornea and the angle. In Axenfeld anomaly, the Schwalbe line is thick and displaced forward onto the cornea.
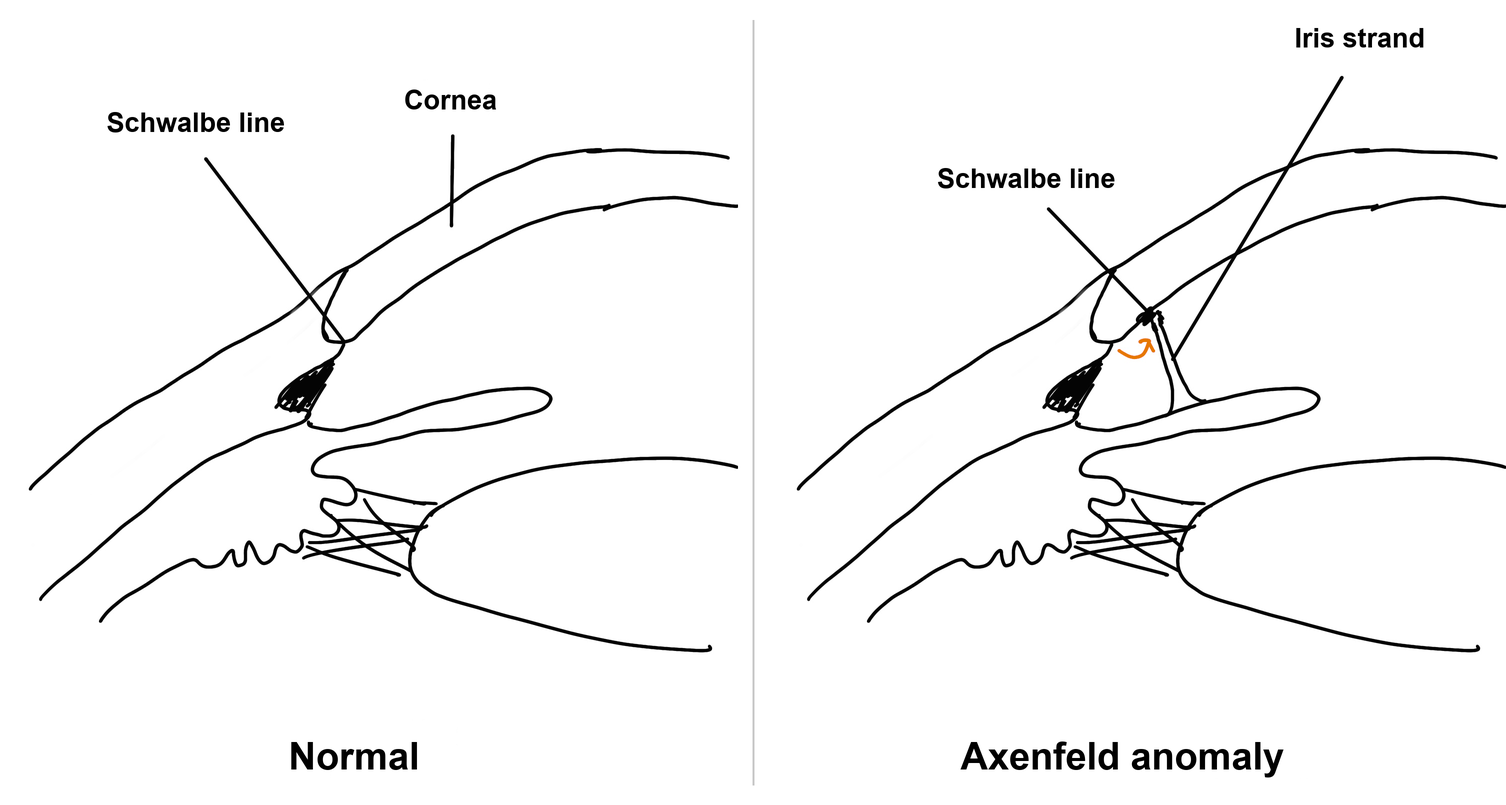
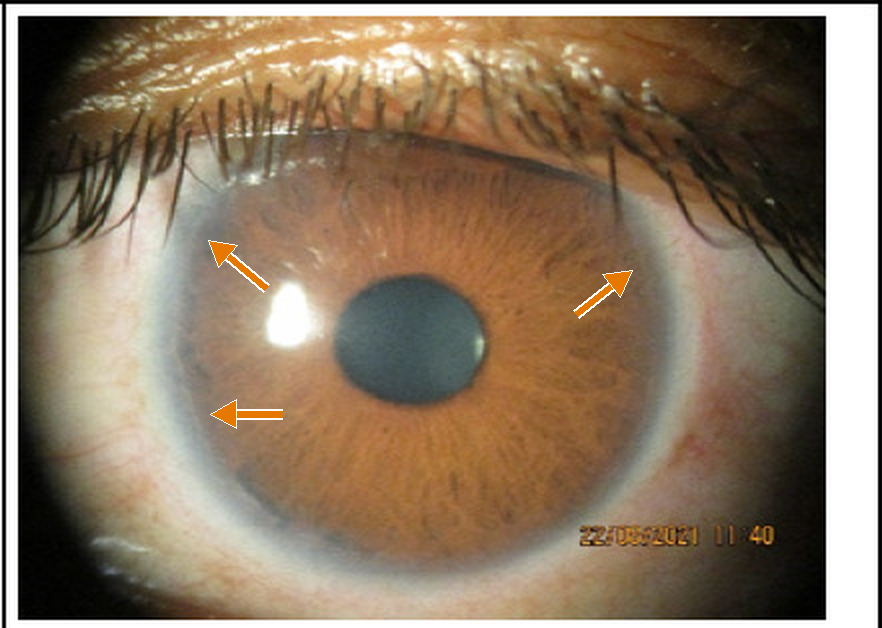
Because the Schwalbe line has moved forward, you can see it from the front as a white line just inside the limbus. This is posterior embryotoxon. When strands of peripheral iris attach to it, it is Axenfeld anomaly. Gonioscopy shows the strands best.
Anterior segment OCT also shows posterior embryotoxon: a thick Schwalbe line juts out from the back of the cornea, sometimes with iris strands attached[3][4].
Rieger anomaly
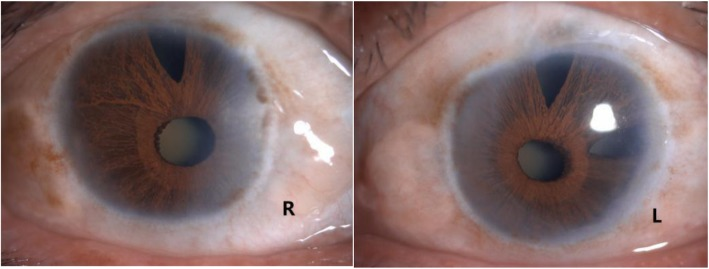
Rieger anomaly is Axenfeld anomaly plus iris changes:
- thin iris stroma (iris atrophy)
- a displaced pupil (corectopia)
- full-thickness iris holes
- ectropion uveae
In severe cases, broad bands of iris stick to the cornea in front of the Schwalbe line.
Rieger syndrome
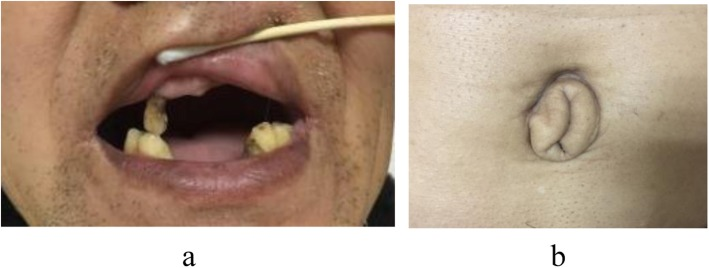
When Rieger anomaly comes with anomalies outside the eye, it is called Rieger syndrome. Look for:
- few teeth (hypodontia) and small teeth (microdontia)
- a flat midface, a broad flat nasal bridge, and widely spaced eyes
- redundant skin around the umbilicus
- less often, hearing loss, developmental delay and other malformations
Treatment
When you find Axenfeld or Rieger anomaly, first check the whole body. Ask a pediatrician to examine the child.
The central cornea stays clear, so the anomaly itself does not reduce vision. The problem is glaucoma. The trabecular meshwork and Schlemm canal are underdeveloped, and glaucoma develops in about 50% of patients. It usually starts in childhood or early adulthood, so keep checking the intraocular pressure (IOP) into adulthood[1].
Drops that reduce aqueous production, such as beta-blockers and carbonic anhydrase inhibitors, work better than drops that increase outflow, such as prostaglandin analogs and pilocarpine.
If eye drops do not control the IOP, surgery is needed:
- Angle surgery (goniotomy or trabeculotomy) works less well than in primary congenital glaucoma.
- Trabeculectomy with an antimetabolite is usually the procedure of choice.
- If it fails, a tube shunt is used[2].
Related conditions
Axenfeld-Rieger syndrome is one of the anterior segment dysgenesis disorders.
Peters anomaly
The center of the cornea is missing its back layers, so the central cornea is opaque. Iris strands run to the edge of the opacity.
Sclerocornea
The cornea turns white like the sclera, either at the periphery or over the whole cornea.
Iridocorneal endothelial (ICE) syndrome
ICE syndrome also causes corectopia, iris holes and peripheral anterior synechiae. But it is acquired and usually affects one eye. If both eyes are affected from birth, think of Axenfeld-Rieger syndrome.
Summary
- Axenfeld-Rieger syndrome is an autosomal dominant anterior segment dysgenesis of tissues that form from neural crest cells. Both eyes are usually affected.
- Axenfeld anomaly: posterior embryotoxon with iris strands. Rieger anomaly: plus iris changes. Rieger syndrome: plus systemic anomalies.
- Posterior embryotoxon alone is common in normal eyes.
- Check the teeth, face and umbilicus, and ask a pediatrician to examine the child.
- Glaucoma develops in about half of patients. Follow the IOP into adulthood.
Figure credits
Posterior embryotoxon: Figure 2 from Thapa M, Gautam P, Sitaula S. JNMA J Nepal Med Assoc 2025;63(284):261-263 (https://doi.org/10.31729/jnma.8951), licensed under CC BY 4.0. Enlarged; arrows added.
Iris, teeth and umbilicus: Figures 1 and 5 from Ma Y, Wu X, Ni S, et al. BMC Ophthalmol 2020;20(1):148 (https://doi.org/10.1186/s12886-020-01406-z), licensed under CC BY 4.0. Used without changes.
The angle drawings are my own.
References
[1] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 11, Glaucoma: iridocorneal dysgenesis.
[2] Yanoff M, Duker JS, eds. Ophthalmology. 5th ed. Elsevier; 2019. Chapter 10.20, Glaucomas secondary to abnormalities of the cornea, iris, retina, and intraocular tumors; Chapter 4.3, Congenital corneal anomalies.
[3] Ramesh PV, Devadas AK, Varsha V, et al. A rare case of unilateral Axenfeld-Rieger anomaly associated with optic disc coloboma: a multimodal imaging canvas. Indian J Ophthalmol. 2022;70(7):2645–2647. PMID 35791186.
[4] Satish N, Sethi S. Asymmetric bilateral Axenfeld-Rieger anomaly misdiagnosed as unilateral iridocorneal endothelial syndrome. Cureus. 2026;18(8):e115031. PMID 42774983.
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.