Eales Disease: Periphlebitis, Nonperfusion and Vitreous Hemorrhage
A young adult has a sudden vitreous hemorrhage in one eye, with no diabetes and no history of trauma. Think of Eales disease. This article explains how to recognize it, how to tell it from branch retinal vein occlusion, and how to treat it.
What is Eales disease?
Eales disease is inflammation around the peripheral retinal veins (periphlebitis) of unknown cause. The inflamed veins then close. It mostly affects healthy young men, especially in South Asia. It is diagnosed by ruling out other diseases that look the same (a diagnosis of exclusion).
It runs in three overlapping stages[1]:
- Inflammatory: sheathing of the peripheral veins (periphlebitis)
- Occlusive: the inflamed vessels close, leaving areas of capillary nonperfusion
- Neovascular: new vessels grow at the edge of the nonperfused retina and bleed into the vitreous
Recurrent vitreous hemorrhage is the main cause of visual loss. Even so, the visual prognosis is good in most patients[1].
Both eyes become involved in most patients (more than 80% during follow-up in large series), often one eye first[2].
Findings
Periphlebitis
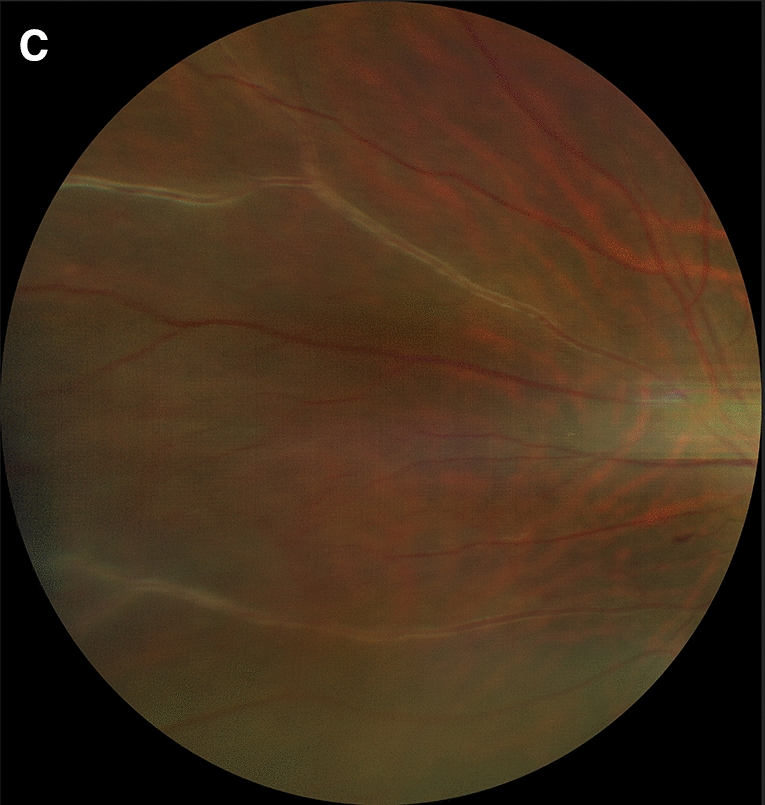
The peripheral veins have white sheathing along their walls. Branches of the inflamed veins can close, with superficial hemorrhages in the same area.
Nonperfusion and neovascularization
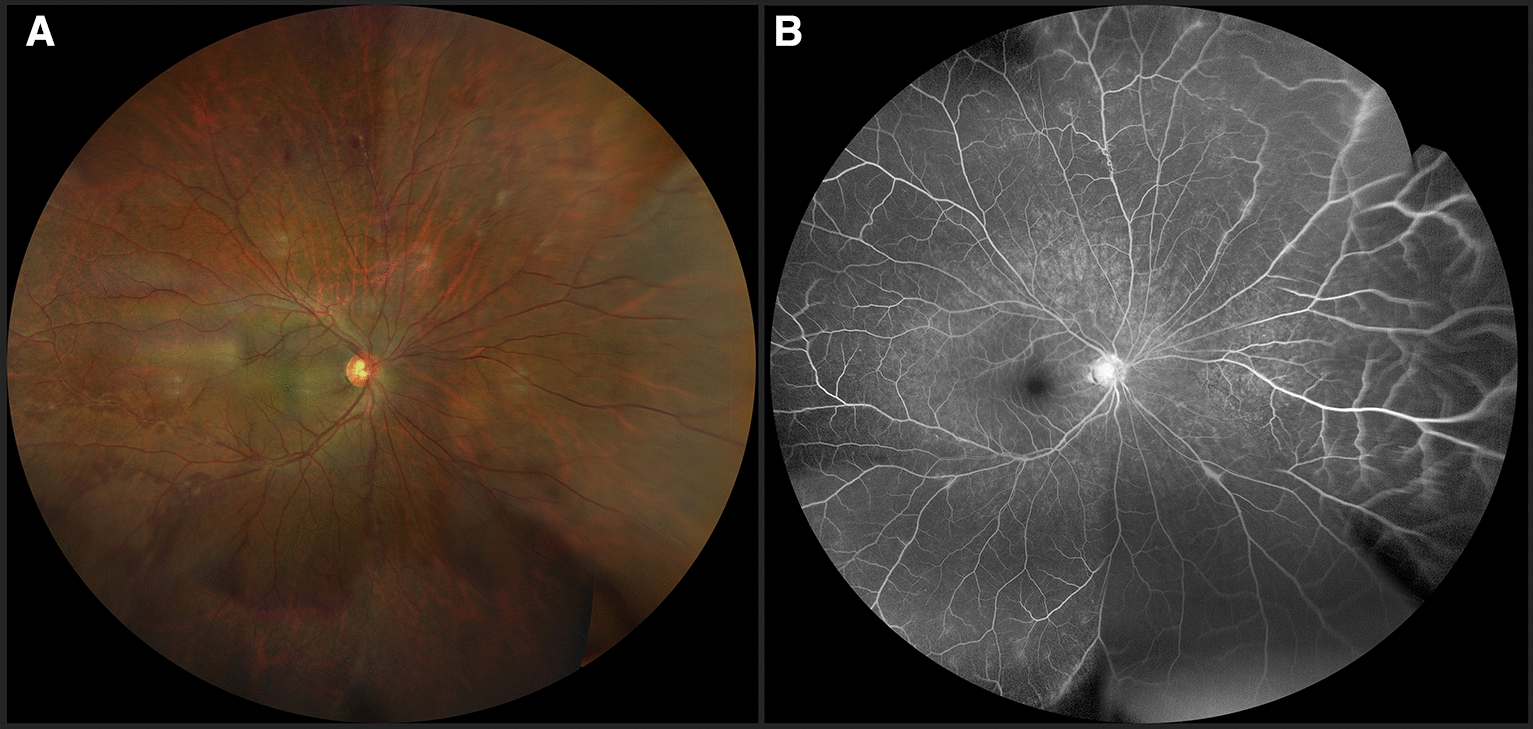
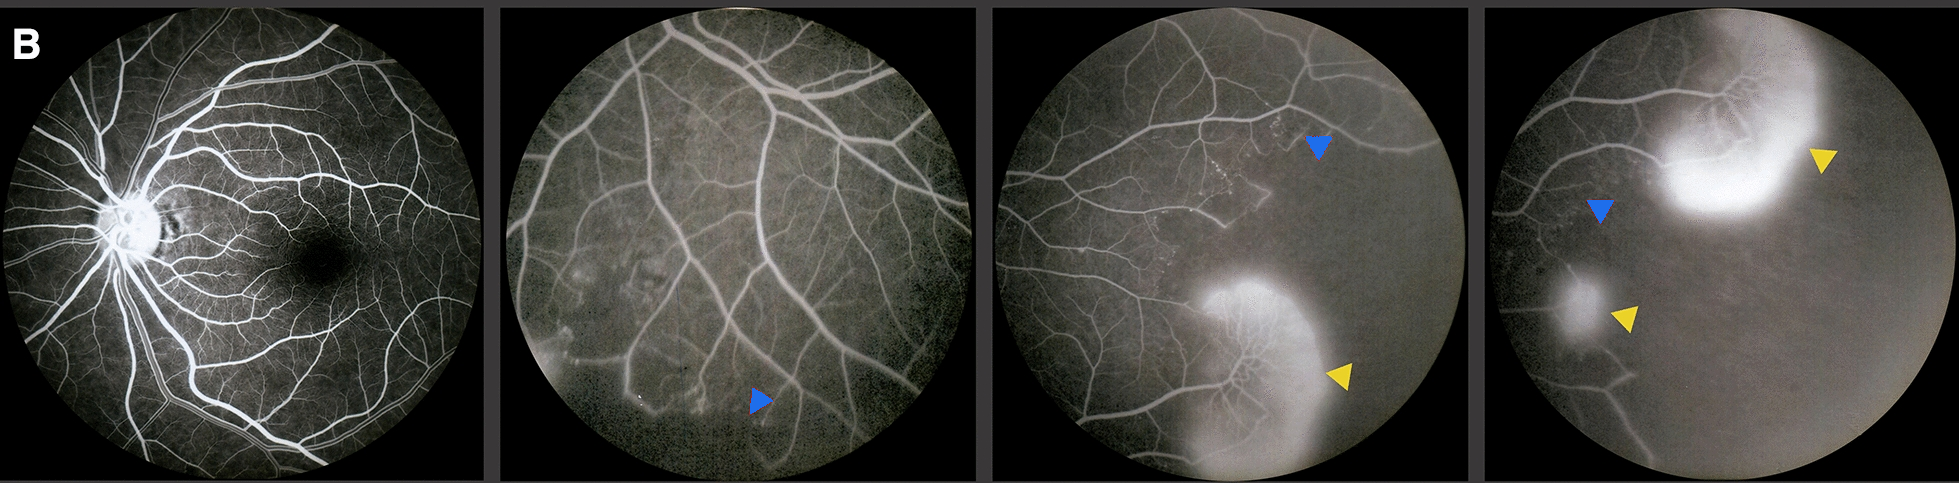
Beyond the sheathed veins, blood stops flowing through the peripheral capillaries (capillary nonperfusion). New vessels grow at the border between perfused and nonperfused retina. On fluorescein angiography (FA), the nonperfused areas are dark, and dye leaks from the new vessels. Wide-field imaging is especially helpful because the changes start in the periphery[1].
How to tell it from branch retinal vein occlusion
Eales disease is sometimes diagnosed as an ordinary branch retinal vein occlusion (BRVO). The difference is where the vein closes. In BRVO, the vein closes at an arteriovenous crossing. In Eales disease, the veins close in the periphery regardless of arteriovenous crossings[3].
Rule out other causes
There is no specific test for Eales disease. Rule out other causes of retinal vasculitis, such as sarcoidosis and tuberculosis, and other causes of peripheral neovascularization, such as sickle cell disease[1].
Tuberculosis needs special attention. Many patients have a strongly positive tuberculin skin test, but a positive test alone does not prove that tuberculosis causes the eye disease[1].
Treatment
The treatment depends on the stage:
- Active periphlebitis: corticosteroids.
- Nonperfusion with new vessels: scatter laser photocoagulation of the nonperfused retina, to reduce the signal that drives new vessels. This is the mainstay, as in Coats disease. Anti-VEGF injections are often added in the neovascular stage.
- Vitreous hemorrhage that does not clear, or tractional retinal detachment: vitrectomy with endolaser[1].
Antituberculous treatment is controversial. Some specialists add it to steroids in patients with a strongly positive tuberculin skin test, to prevent reactivation of a past infection[1].
Summary
- Eales disease is inflammation around the peripheral retinal veins of unknown cause, mostly in healthy young men. It is a diagnosis of exclusion.
- It runs from periphlebitis to nonperfusion to neovascularization, and recurrent vitreous hemorrhage is the main problem.
- Unlike BRVO, the veins close regardless of arteriovenous crossings.
- Do FA of both eyes. A fellow eye that looks normal can already have nonperfusion.
- Treat by stage: steroids for active inflammation, laser for nonperfusion with new vessels, and vitrectomy for hemorrhage that does not clear.
Figure credits
All figures: Figures 2C, 4 and 3B from Murillo López S, Medina Medina S, Murillo López F. Int J Retina Vitreous 2022;8(1):3 (https://doi.org/10.1186/s40942-021-00354-0), licensed under CC BY 4.0. Figure 2C and the B row of Figure 3 cropped; in Figure 3B, red arrowheads recolored blue.
References
[1] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 13, Retinal vascular disease: Eales disease.
[2] Murillo López S, Medina Medina S, Murillo López F. Eales’ disease: epidemiology, diagnostic and therapeutic concepts. Int J Retina Vitreous. 2022;8(1):3. PMID 34983678.
[3] Nussenblatt RB, Whitcup SM. Uveitis: Fundamentals and Clinical Practice. 4th ed. Mosby Elsevier; 2010. Chapter 27, Retinal vasculitis.
Which retinal layer makes which wave, the three abnormal patterns, and the dark-adaptation trap to check before you report “negative” — on one page, by email. One email when I publish something new, about once a month. Unsubscribe anytime.