Vogt-Koyanagi-Harada (VKH) Disease: OCT, FA, ICGA and Treatment
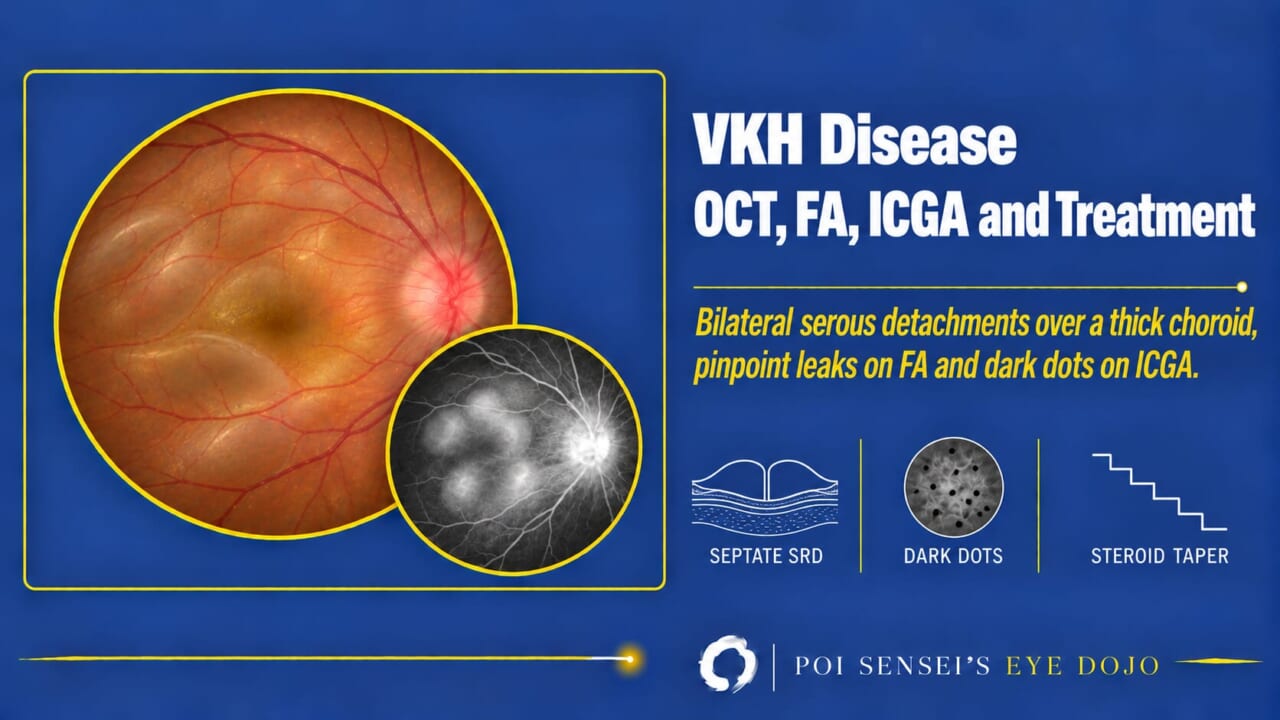
Both eyes have blurred vision, and the patient had a headache and ringing in the ears a few days ago. The OCT shows serous retinal detachments in both eyes. This article shows how to read Vogt-Koyanagi-Harada (VKH) disease on OCT, fluorescein angiography and indocyanine green angiography (ICGA), and how it is treated.
- Who: inflammation in both eyes, with headache, tinnitus or hearing loss. Most patients have darker skin (Asian, Hispanic, Native American).
- OCT: serous retinal detachments, often divided by septa, over a thick choroid.
- Fluorescein angiography: many pinpoint leaks that pool under the retina, and a bright disc.
- ICGA: many small dark dots.
- Swollen discs but no detachment? Check the choroid before calling it optic neuritis.
What is VKH disease?
Vogt-Koyanagi-Harada disease is an autoimmune attack on melanocytes, the pigment cells of the uvea, inner ear, meninges, skin and hair. In the eye it causes inflammation of the whole uvea in both eyes (bilateral granulomatous panuveitis)[1].
VKH mainly affects people with darker skin, such as Asian (especially Japanese), Hispanic and Native American people[1][2]. In Japan it is one of the main causes of uveitis. It is uncommon in people of European descent.
Typical cases, with bullous serous retinal detachments in both eyes, are easy to diagnose. Without the detachments it can be hard.
Symptoms
Outside the eye, meningitis and inner ear involvement cause headache, vertigo, tinnitus and sensorineural hearing loss.
Months after onset, the attack on melanocytes turns the skin, scalp hair, eyebrows and eyelashes white (vitiligo and poliosis), and hair can fall out (alopecia).
Findings
Anterior segment
In the acute phase, the ciliary body swells and the anterior chamber becomes shallow. Ultrasound biomicroscopy shows the ciliary body edema and a ciliochoroidal detachment. The lens and iris move forward, so the chamber becomes shallow and the eye becomes myopic.
The anterior chamber inflammation is granulomatous. There may be mutton-fat keratic precipitates. Posterior synechiae all around the pupil can push the iris forward (iris bombé).
OCT
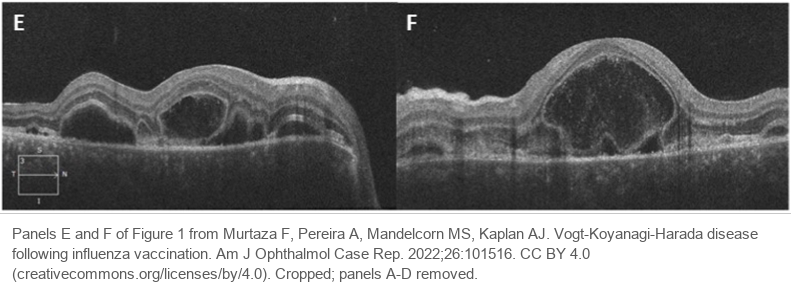
The inflammation in VKH is mainly in the choroid. In the acute phase, OCT shows a thick choroid. The choroid can also look wavy (choroidal folds). This points to inflammation in the choroid.
If you suspect VKH but the choroid is not thick, consider another disease, such as posterior scleritis. Posterior scleritis is hard to tell from VKH, because it also causes serous retinal detachments. Ultrasound or CT helps: it shows a thick posterior sclera in posterior scleritis[1][2].
Fluid also collects under the retina in both eyes (serous retinal detachment). Large, dome-shaped detachments, or detachments split into several pockets by thin walls (septa), are typical of VKH[1].
Fundus, fluorescein angiography and ICGA
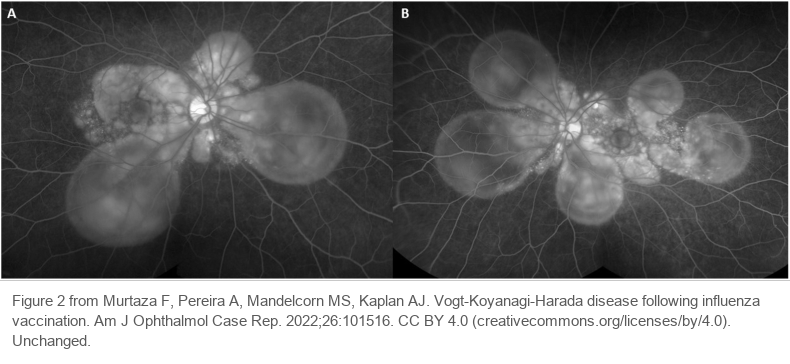
The optic disc is often red and swollen. On fluorescein angiography, it leaks dye and looks bright. In the acute phase, fluorescein angiography shows many pinpoint leaks at the level of the retinal pigment epithelium. Later in the study, the dye pools under the detached retina[1].
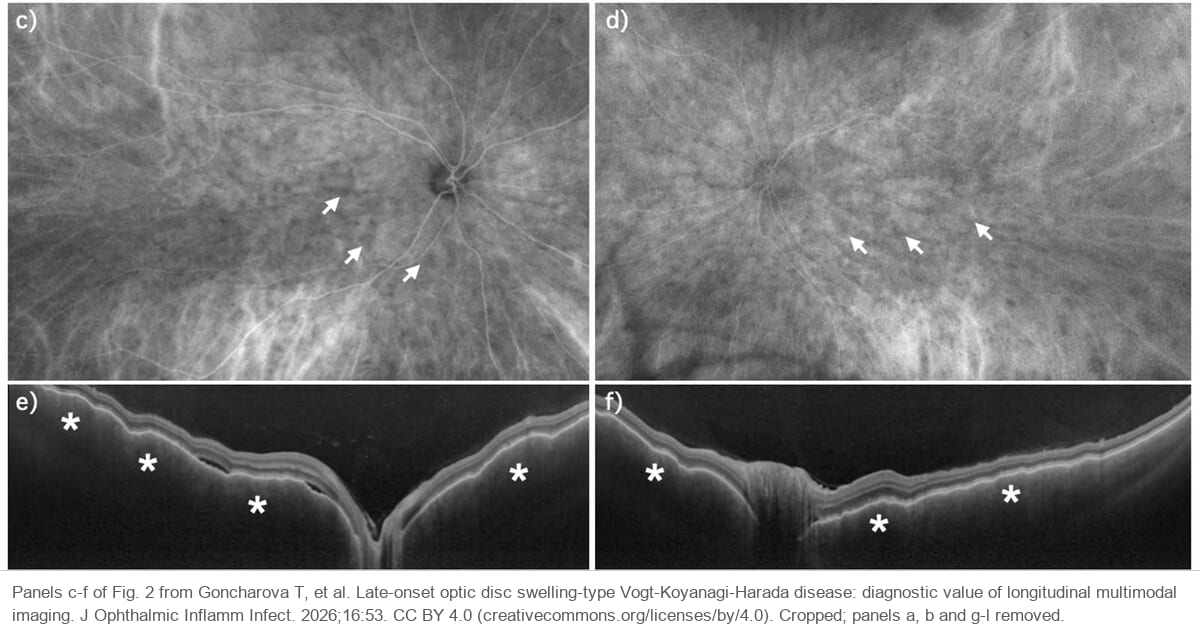
ICGA shows the choroidal vessels. In VKH it shows dark dots: many small, round dark spots spread over the fundus. They fade with treatment[2].
Some patients have swollen, red discs in both eyes but no serous detachment. This is called the disc swelling type. It is often mistaken for bilateral optic neuritis, and the diagnosis is delayed.
Convalescent phase
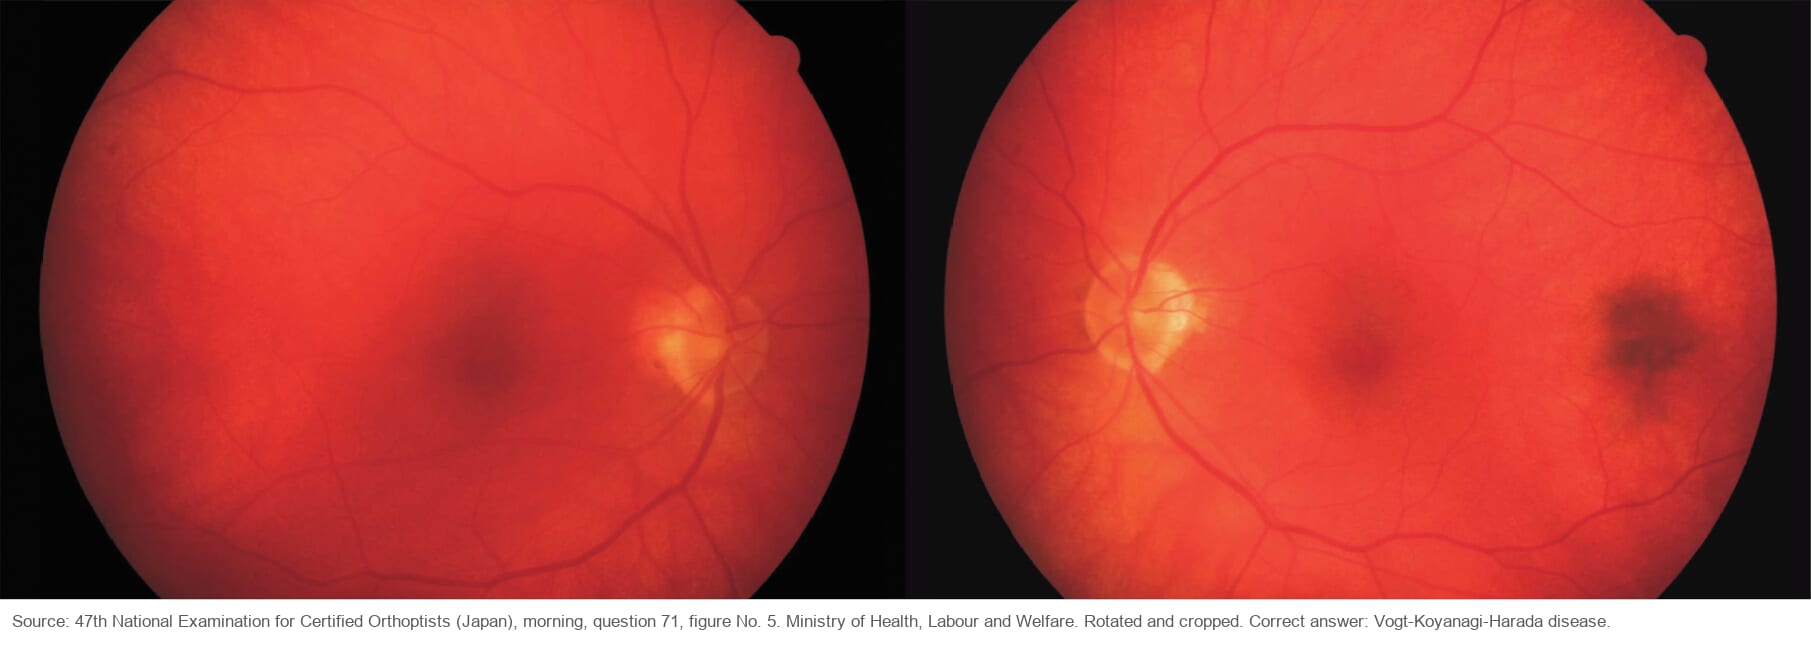
As the inflammation settles, the choroid loses its pigment and the whole fundus looks orange-red. This is the well-known sunset glow fundus.
Small, round, white atrophic spots can also appear in the peripheral fundus, like those seen after sarcoidosis.
Cerebrospinal fluid
VKH causes an aseptic meningitis, so the cerebrospinal fluid shows more lymphocytes than normal (lymphocytic pleocytosis). It is seen in about 80% of patients within one week of onset[2].
Treatment
Treatment often starts with high-dose steroid pulse therapy, such as intravenous methylprednisolone 1000 mg a day for 3 days[1].
Then oral prednisolone is started at about 1 mg/kg a day (60 mg a day for a 60 kg patient). Taper it slowly. If you drop the dose too fast, the inflammation comes back.
| Daily dose | Reduce by | Every |
|---|---|---|
| 40 mg or more | 10 mg | 1–2 weeks |
| 20–40 mg | 5 mg | 1–2 weeks |
| 10–20 mg | 2.5 mg | 1–4 weeks |
| Below 10 mg | 1–2.5 mg | 1–4 weeks |
The maintenance dose should be 10 mg a day or less. The table is adapted from an expert panel’s recommendations[3].
The whole taper takes at least 6 months. Some patients still relapse during the taper. In that case, cyclosporine or methotrexate is added. For patients whose disease keeps going, adalimumab can be considered.
Summary
- VKH: an autoimmune bilateral granulomatous panuveitis, with headache, tinnitus and hearing loss.
- Acute angle closure in both eyes: think of VKH.
- OCT: a thick choroid, and serous detachments that are bullous or divided by septa.
- Fluorescein angiography shows pinpoint leaks that pool under the retina. ICGA shows dark dots.
- Swollen discs without detachment: check the choroid before calling it optic neuritis.
- High-dose steroids, often starting with a pulse, then a slow oral taper over at least 6 months.
Figure credits
Optical coherence tomography and fluorescein angiography: panels E and F of Figure 1, and Figure 2, from Murtaza F, Pereira A, Mandelcorn MS, Kaplan AJ, Am J Ophthalmol Case Rep 2022;26:101516, licensed under CC BY 4.0. Figure 1 was cropped; Figure 2 is unchanged.
ICGA and optical coherence tomography of the disc swelling type: panels c to f of Fig. 2 from Goncharova T, et al., J Ophthalmic Inflamm Infect 2026;16:53, licensed under CC BY 4.0. Cropped; panels a, b and g to l removed.
Sunset glow fundus: reproduced from the 47th National Examination for Certified Orthoptists (Japan), morning session, question 71 (figure No. 5), published by the Ministry of Health, Labour and Welfare. Rotated and cropped.
References
[1] Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 10th ed. Elsevier; 2025. Chapter 12, Uveitis: Vogt-Koyanagi-Harada (VKH) syndrome.
[2] Yanoff M, Duker JS, eds. Ophthalmology. 5th ed. Elsevier; 2019. Chapter 7.17, Vogt-Koyanagi-Harada disease.
[3] Jabs DA, Rosenbaum JT, Foster CS, et al. Guidelines for the use of immunosuppressive drugs in patients with ocular inflammatory disorders: recommendations of an expert panel. Am J Ophthalmol. 2000;130(4):492-513. PMID 11024423.
[4] Zhang HA, Yuan AT, Chiasson N, et al. Immune checkpoint inhibitor-associated Vogt-Koyanagi-Harada-like syndrome: a descriptive systematic review. J Ophthalmic Inflamm Infect. 2025;15:44. PMID 40354015.